The peptide craze rests on a scientific half-truth
You dont have to let these challenges define your journey
Normalization of Muc5b ameliorates airway mucus plugging during persistent Pseudomonas aeruginosa infection in the CFTR/ rat
In addition, B12 deficiency-associated fatigue is often accompanied by other symptoms such as numbness and tingling, cognitive impairment (memory and concentration problems), mood swings (depression), skin changes (pale skin), shortness of breath, or fast heart rate
Many clinicians recommend peptide therapy alongside structured PT for best outcomes

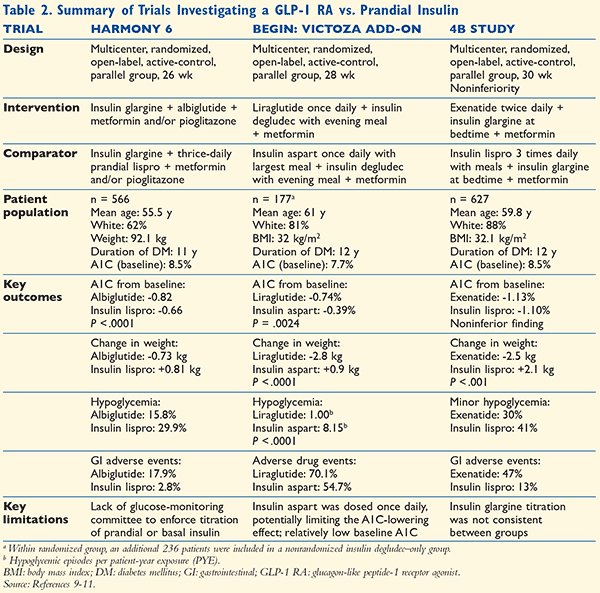
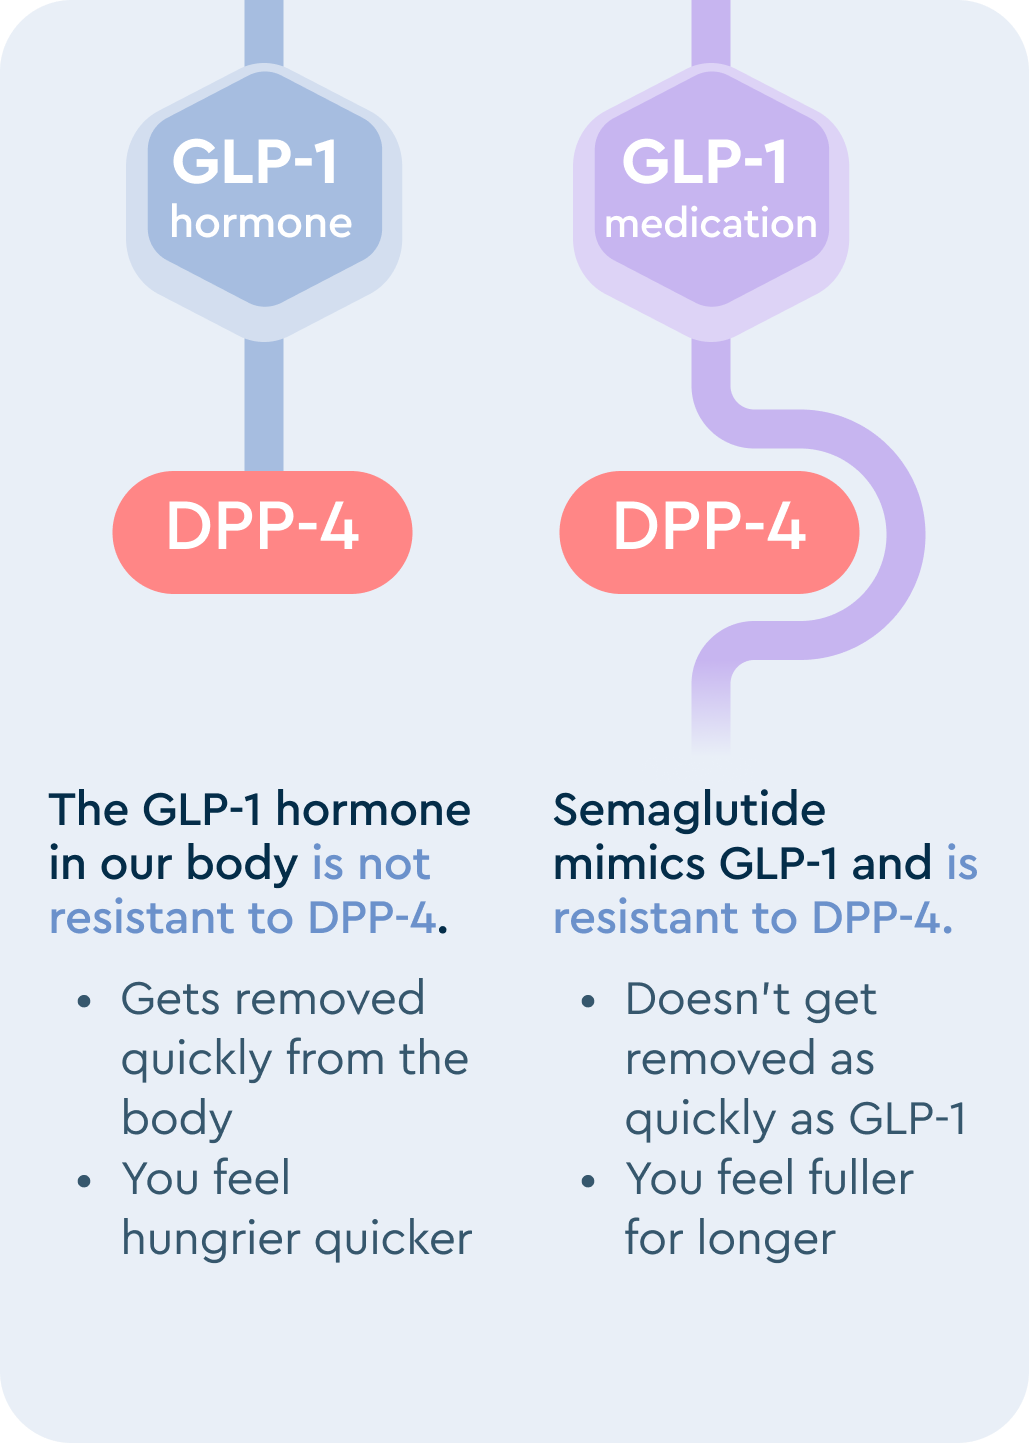
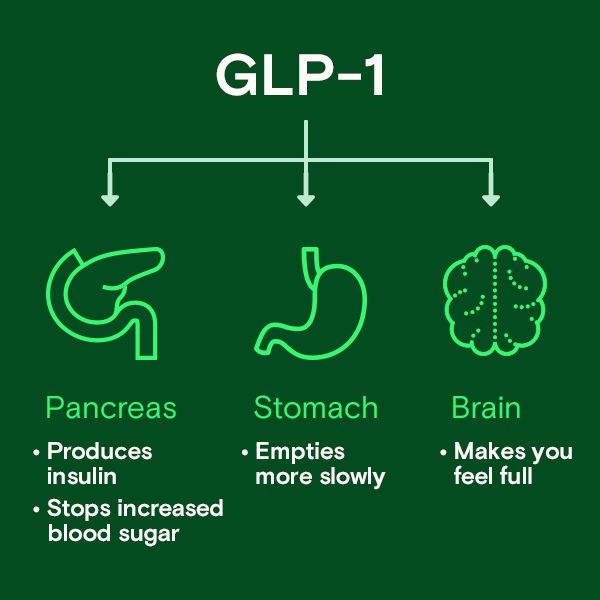
First principles: when stacking makes sense vs when its just noise Heres the simplest clinical lens I know: A stack can be reasonable when it meets all 4 criteria Different primary mechanisms (true complement, not redundancy) A clear problem statement (e.g., Im losing weight but also losing lean mass vs I want to feel optimized) Human evidence exists for at least one component and the combined physiology isnt contradictory You can monitor outcomes and safety objectively (labs, body composition, symptoms, performance, vitals) A stack is usually unjustified when it has any of these patterns Redundant signaling (two compounds tugging the same rope) Unmonitorable goals (recovery, vitality, anti-aging without measurable endpoints) Axis overstimulation (especially GH/IGF-1 signaling) Quality/sterility uncertainty (common with online research vials) No exit plan (no defined stop criteria or reassessment window) The 4 major peptide lanes youll see in stacking culture Most stacks are built from some combination of these buckets: Incretin/metabolic lane (GLP-1/GIP-based pharmacologytypically FDA-approved drugs rather than peptides in the wellness sense) GH/IGF-1 lane (GHRH analogs and ghrelin receptor agonists/secretagogues) Lipolytic fragments/modulators (often marketed for fat loss