Protocol 2: the tirzepatide micro-step escalation Goal: Avoid the dramatic side effects common with standard 2.5 mg escalation jumps Schedule (compounded tirzepatide required): Weeks 1-4: 2.5 mg weekly Weeks 5-8: 3.0 mg weekly Weeks 9-12: 3.75 mg weekly Weeks 13-16: 5.0 mg weekly Weeks 17-20: 6.25 mg weekly Weeks 21-24: 7.5 mg weekly Continue escalating by 1.25-2.5 mg every 4 weeks as needed Why the plotter supports this: The standard jump from 2.5 mg to 5 mg produces a transition spike where your first-week peak at 5 mg can exceed the eventual 5 mg steady-state peak by 15-25%
Por estes motivos, tm vindo a ser cada vez mais utilizados no tratamento destas doenas crnicas
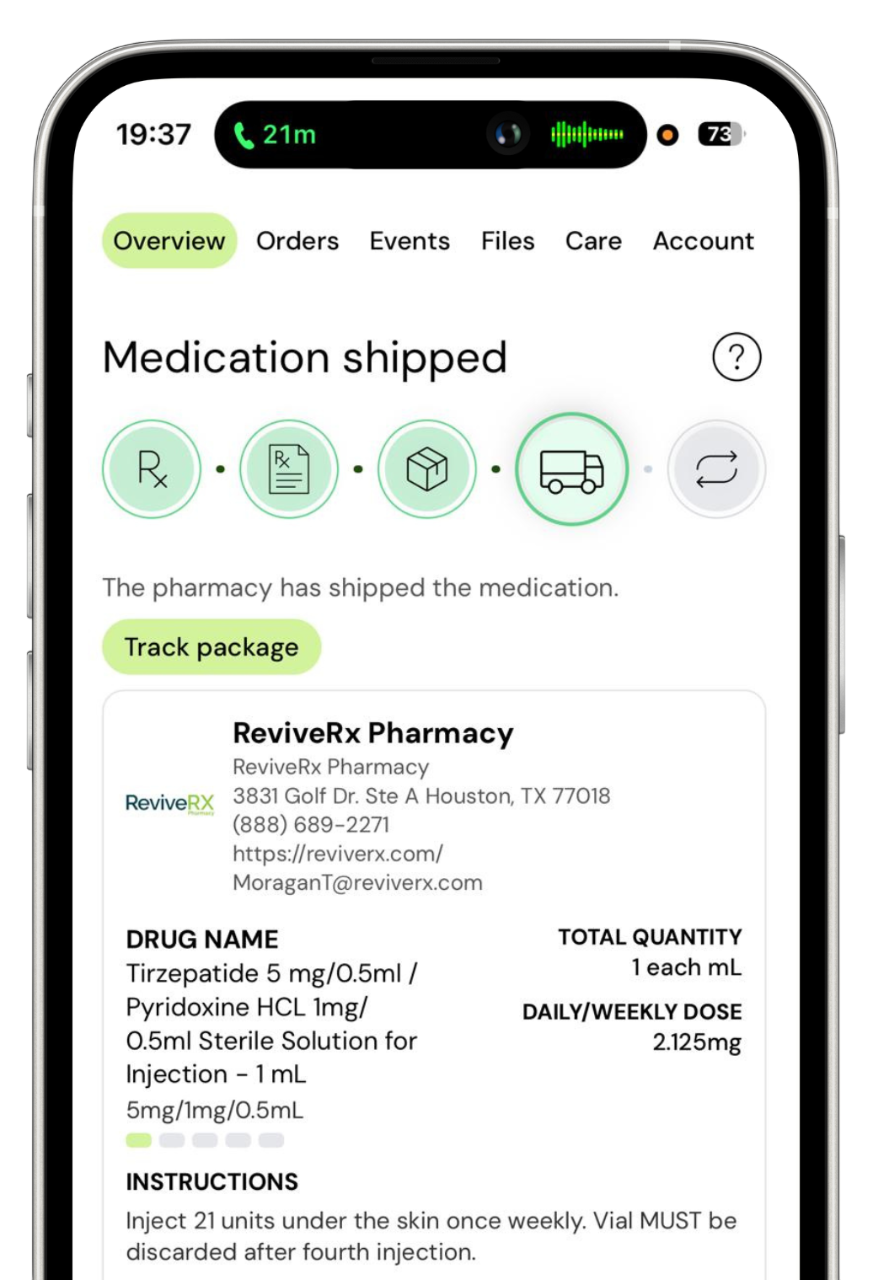
The B6 in the compound supports this transition by maintaining the enzymatic pathways involved in energy extraction from macronutrients
For those on TRT and considering peptides, community sources commonly describe this layering order: Stabilize TRT first (8-12 weeks) with testosterone levels and estradiol dialed in Add one GH peptide ipamorelin or CJC-1295, described as the safest starting point Stack GHRH + GHRP adding the complementary class for fuller GH-axis coverage (see GHRH vs GHRP for why both matter) Add recovery peptides as needed BPC-157 and/or TB-500 for specific injuries Metabolic add-ons MOTS-c for body composition, tesamorelin for visceral fat Functional peptides PT-141 for libido where testosterone alone is described as insufficient Community sources consistently advise against adding more than one new peptide at a time, describing a 4-week gap between additions so effects (and side effects) can be attributed correctly
Current evidence does not support a need for dose adjustment in coadministration of digoxin and GLP1RAs
Our knowledge of insurance providerslike UnitedHealthcare, Cigna, Blue Cross Blue Shield, Aetna, Medicare, and Medicaidmeans you receive clear answers about your coverage