Positive None

The distribution map of SEMA in the central nervous system shows a greater presence in the septal nuclei compared to LIRA.19 In addition to reducing food intake, SEMA has proven effective in modulating food preferences,12 likely through dopaminergic activation of the ventral tegmental area and a reduction in endocannabinoid tone.19 The subsequent activation of the parabrachial nucleus and other neural circuits involved in the hedonic regulation of food intake may be specific to SEMA, potentially helping to explain its differences from LIRA.19 The mechanisms involved in the improvement of glycaemic control by LIRA 3 mg and SEMA 2.4 mg are related to their incretin and glucagonostatic effects inherent to GLP-1 receptor agonism,3 as well as to those derived from weight loss, reduction in fat mass, and their associated consequences.20 Effects on other comorbidities The SCALE programme shows that the apnoea-hypopnoea index reduces in cases of sleep apnoea syndrome when LIRA is used instead of a placebo (12.2 vs 6.1, p = 0.015).21 The contribution of weight loss to the effects of LIRA treatment in the SCALE programme varies

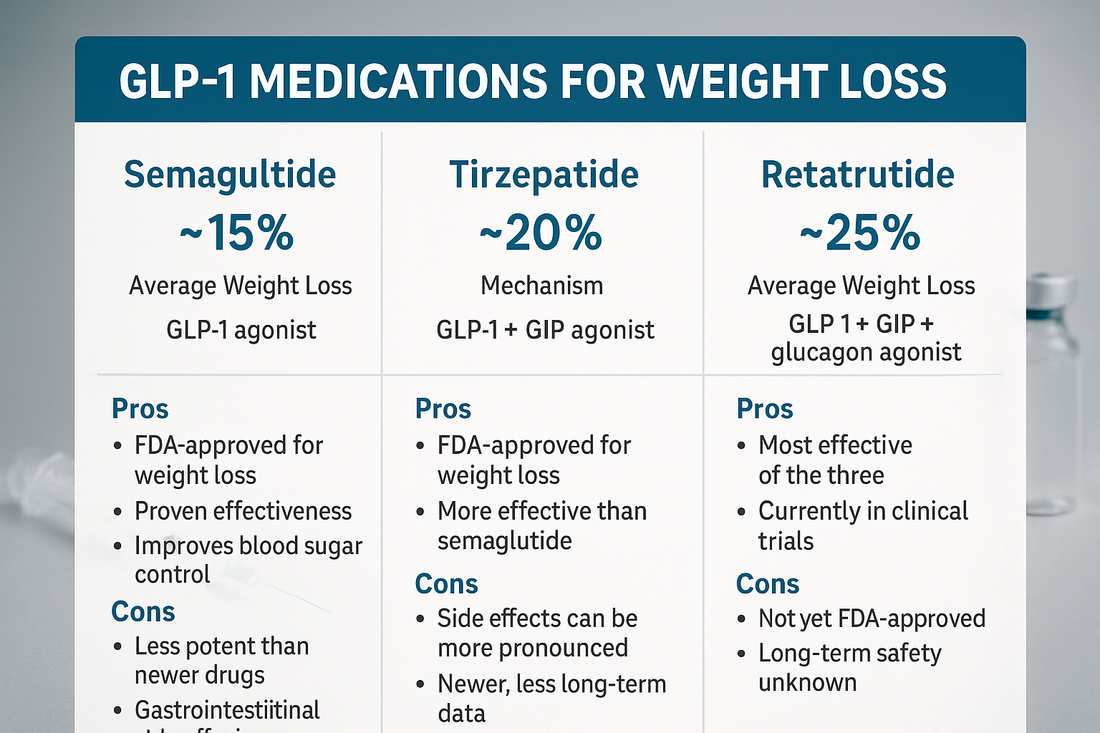
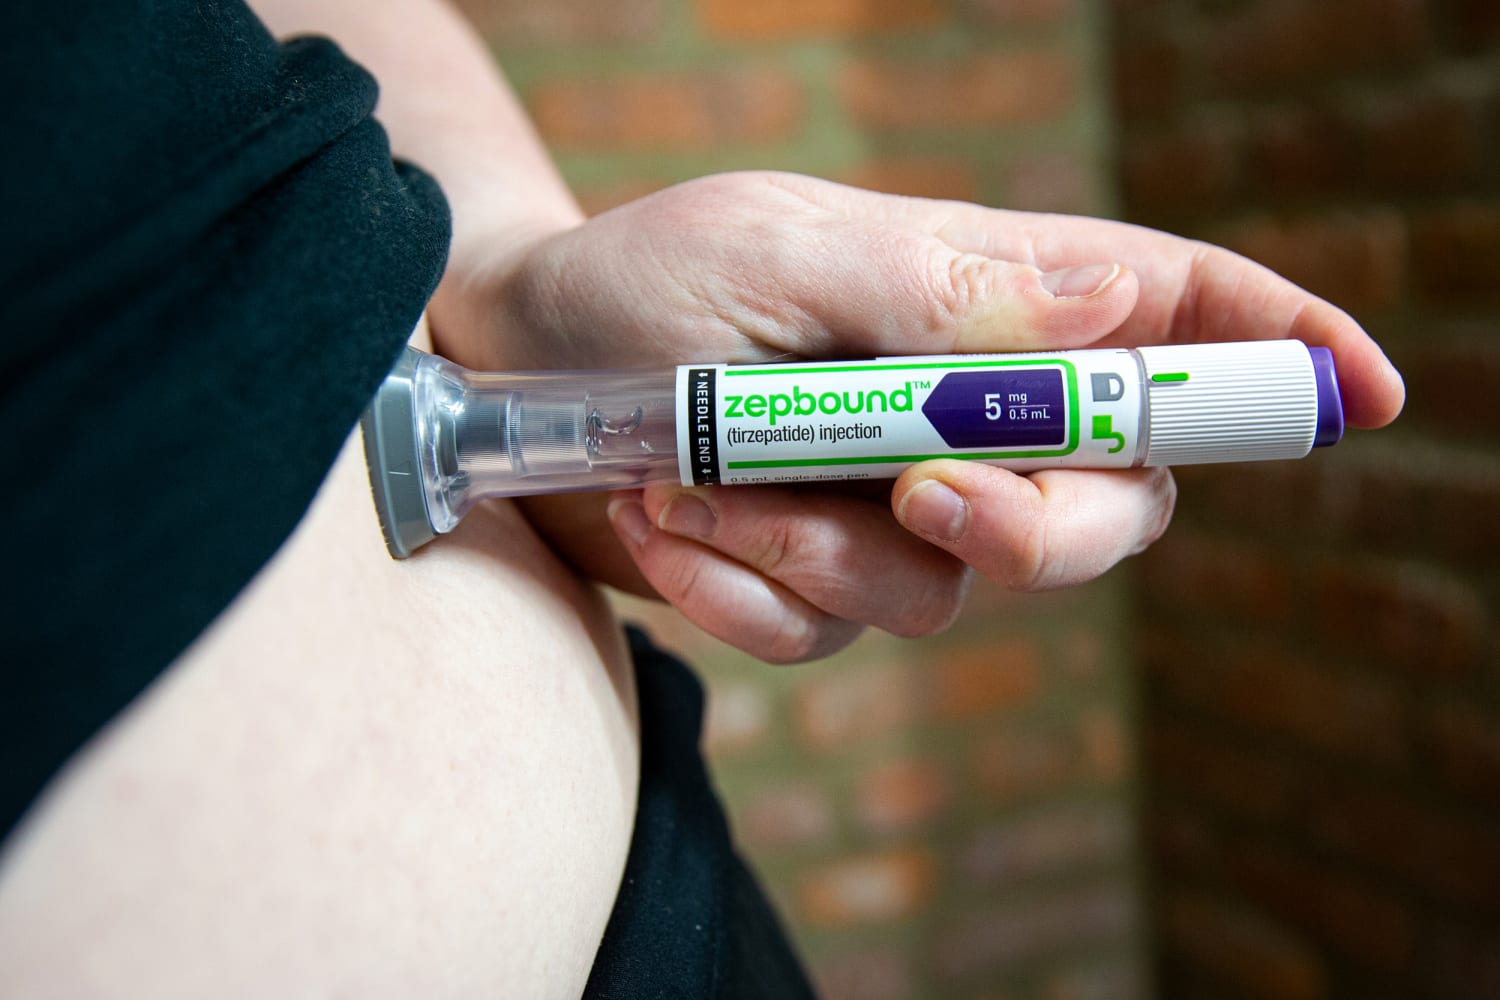
This is not surprising, considering that tirzepatide and semaglutide evoked more pronounced TBWL and also have glucose-lowering effects by slowing gastric emptying, stimulating insulin secretion and inhibiting glucagon secretion in a glucose-dependent manner, independent of their effects on body weight 50,51
Some healthcare providers consider this combination for patients who have hit a weight loss plateau on a GLP-1 medication alone
COVID-19, coronavirus disease 19
When expressed in the CHO cell line, the hKOR was demonstrated to undergo a time- and concentration-dependent uncoupling from G proteins but with a moderate impact on the inhibition of ACase (a two-fold increase of the EC 50 value of the KOR agonist U50488) (Zhu et al., 1998)