Likely related to niacin-like vasodilation from rapid B12 absorption
Shorter strands
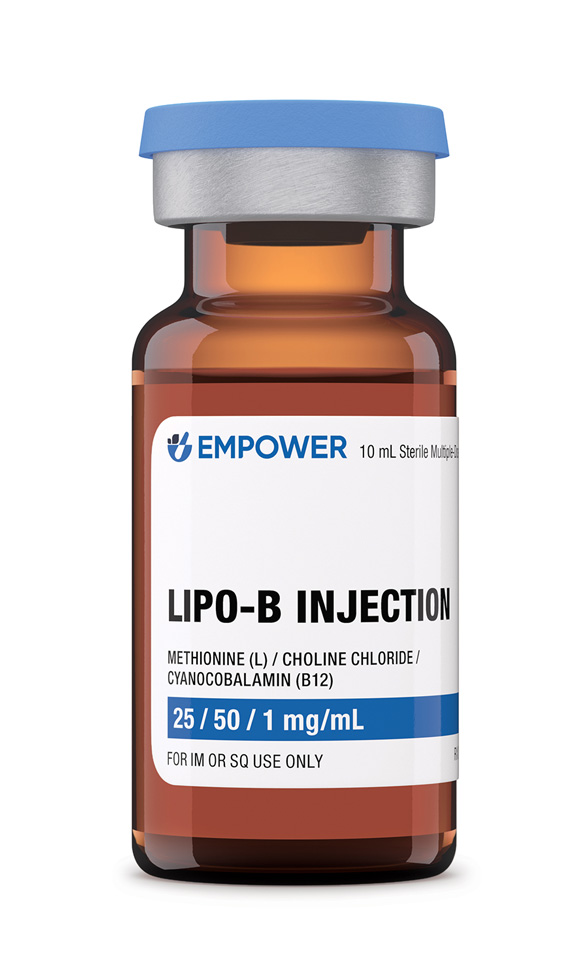
However, for patients who want nutritional metabolic support especially those with identified deficiencies in choline or B vitamins they may provide a reasonable complement to evidence-based weight management strategies
Both peptides are not approved for routine human use (sold for research purposes) and are banned in competitive sports [10]

Essential B Vitamins for MTHFR B9 (Folate) Form: 5-MTHF (methylfolate), NOT folic acid Dose: 400-800mcg daily minimum (up to 5mg for some conditions) Why: Bypasses MTHFR enzyme bottleneck Look for: Quatrefolic, Metafolin, or L-5-MTHF on labels B12 (Cobalamin) Form: Methylcobalamin OR hydroxocobalamin (avoid cyanocobalamin) Dose: 500-1000mcg daily minimum (up to 5000mcg for deficiency) Why: Essential cofactor for methylation, lowers homocysteine Choose methylcobalamin for: Direct methylation support Choose hydroxocobalamin for: Sensitive individuals, histamine issues B6 (Pyridoxine) Form: P5P (pyridoxal-5-phosphate), the active form Dose: 5-50mg daily, but will be highly individualised Why: Supports transsulfuration pathway, prevents homocysteine buildup Avoid: Regular pyridoxine HCl (requires conversion) B2 (Riboflavin) Form: Riboflavin or riboflavin-5-phosphate Dose: 10-100mg daily (higher doses for C677T homozygous) Why: Required cofactor for MTHFR enzyme function Benefit: Can improve MTHFR enzyme efficiency up to 50% Supporting Nutrients Magnesium Zinc Choline or TMG (Betaine) How to Choose a B12 Supplement for MTHFR Look for methylcobalamin or hydroxocobalamin Avoid cyanocobalamin Check for fillers or artificial folic acid Sublingual/ spray forms often absorb better Frequently Asked Questions About B12 and MTHFR Which form of B12 is best for MTHFR
Let's just reflect on this basic process